
How physicians can help improve declining childhood immunization coverage rates in BC
Issue: BCMJ,
vol. 68, No. 8, October 2026
|
Pages 290,291 |
BC Centre for Disease Control
Immunization coverage assessments are conducted to measure the percentage of people who have received certain vaccines. The assessments are used to:
- Understand population-level protection against vaccine-preventable diseases.
- Explore potential reasons for low vaccine coverage.
- Identify communities at higher risk for outbreaks.
- Inform population-level interventions, including resource allocation.
Routine childhood immunization coverage is assessed annually at four key milestones: age 2, age 7, grade 6, and grade 9. Coverage estimates for individual antigens are calculated for each milestone, and the proportion of children considered up to date for all antigens is presented for ages 2 and 7. Annual coverage estimates, historical coverage trends, and reasons for nonimmunization are published on the BC Centre for Disease Control website.[1]
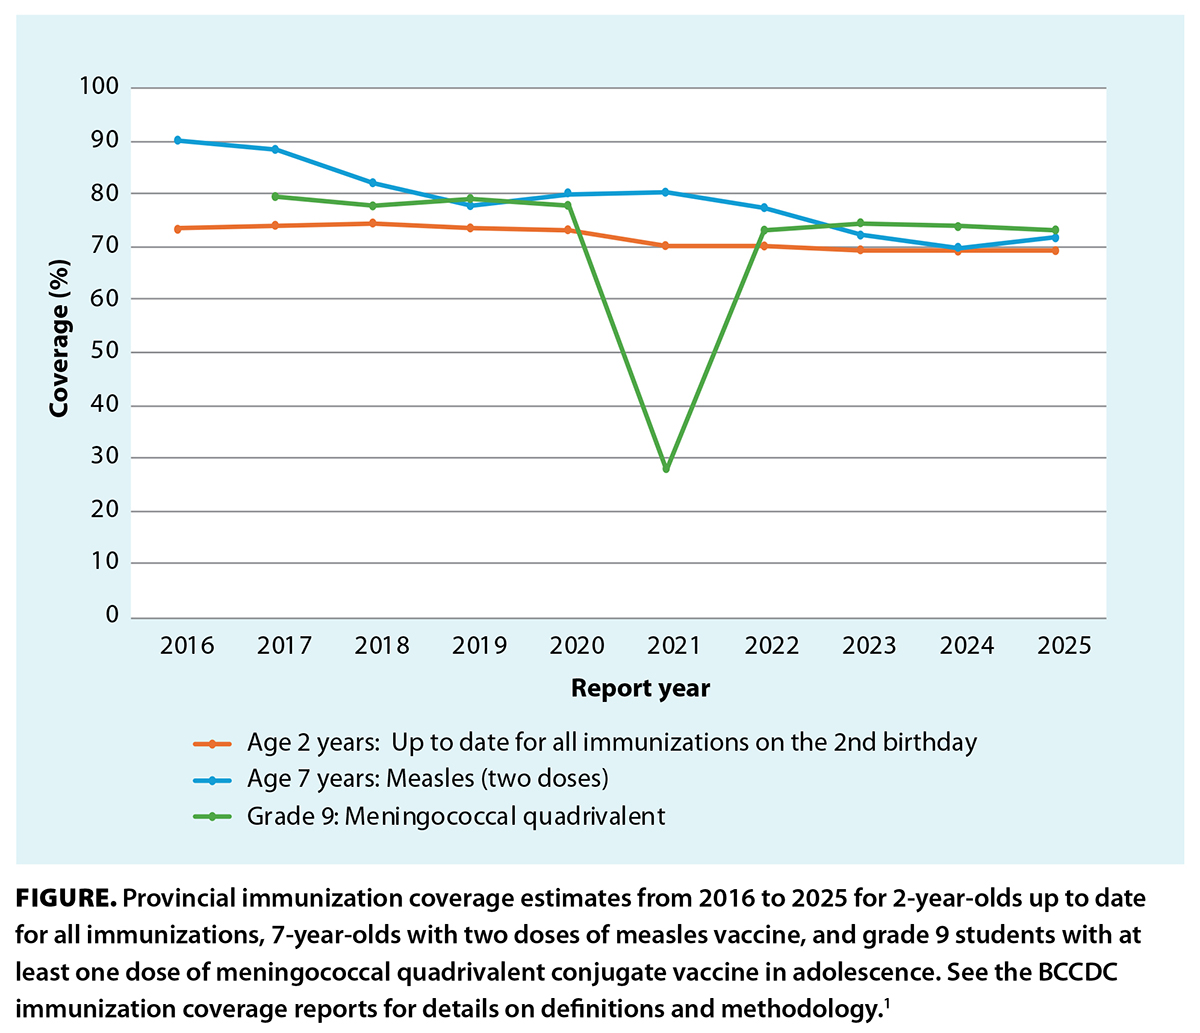 For most routine childhood vaccines, provincial coverage rates have generally declined from 2016 to 2025.[2] Two-dose measles vaccine coverage at age 7 decreased from 90% in 2016 to 72% in 2025, while the proportion of children considered up to date for all routine immunizations at age 2 decreased from 73% in 2016 to 69% in 2025 [Figure].[2] Recent years have seen recovery from lows observed during the COVID-19 pandemic attributable to pandemic-related service disruptions, although coverage rates have not returned to prepandemic levels.[2] Uptake of the meningococcal quadrivalent conjugate vaccine in grade 9—previously holding steady at 78% in 2017 to 79% in 2020—dropped to 28% in 2021 due to interruption of school-based immunization clinics.[2] Rates subsequently recovered to 73% in 2022 and 74% in 2025 [Figure].[2] Declines in childhood immunization coverage have been similarly observed in other provinces in Canada.[3]
Reasons for lower immunization coverage
Reasons for lower immunization coverage estimates are multifactorial and include documentation gaps, barriers to vaccine access, and other structural and systemic factors. Coverage estimates are based on vaccine doses recorded in the Provincial Immunization Registry. However, not all vaccinations are recorded. Doses administered by family physicians and in acute care settings are generally not recorded or are delayed being recorded unless they are reported separately to Public Health, documented using the Immunization Entry Form (via eForms), or submitted via the provincial immunization record portal. Immunization records for people new to BC (including those from another province or territory) are also not automatically captured in the registry. Of the 2024 and 2025 cohorts, 9% to 11% at ages 2 and 7 and 2% to 4% in grades 6 and 9 had no records in the registry and are therefore reported as unimmunized.
Coverage rates may also be influenced by access to vaccination services. School-based vaccination programs have long supported access by removing the need to book appointments and travel to vaccination sites[4] and have played a key role in vaccine uptake. This is demonstrated by the reduction in grade 9 immunization coverage as a result of service disruptions during the pandemic as well as by the increase of two-dose measles vaccination coverage from age 7 (80% in 2021) to grade 6 (89% in 2025) among roughly the same cohorts.[2]
While coverage rates are not stratified by sociodemographic factors, inequities in structural and social determinants of health are long recognized as contributing to unequal infectious disease burden as well as differential access to and uptake of vaccination. For example, rural, remote, and Indigenous communities face inequitable access to vaccination. People living with disabilities face various barriers to access, while newcomers face challenges finding accurate information that meets cultural and linguistic needs. Historic and ongoing medical racism and discrimination also negatively affect trust and vaccine acceptance.[4]
Moreover, while vaccine mis- and disinformation are not new phenomena, the relationship between trust, mis- and disinformation, and vaccination may be particularly complex for populations already experiencing mistrust in health care or the government, particularly in the context of increased polarization of vaccination across digital and social media platforms.[4]
What physicians can do to improve vaccination coverage
Many initiatives to support vaccination focus on individual-level factors affecting vaccine uptake rather than access to vaccines. Without considering access, differential vaccine uptake may be incorrectly attributed to low vaccine acceptance rather than structural issues, placing undue responsibility on individuals without recognizing the broader systems and determinants influencing vaccination.[4] Understanding structural barriers to vaccine access enables physicians to tailor their approach to populations facing intersecting inequities, including the following.
Offering and promoting low-barrier vaccination: Resources are needed to book vaccine appointments, travel to appointments, and cover other vaccination-related costs (e.g., time off work). Physicians can work with patients to identify and address these barriers by co-delivering vaccines with other health services, reducing missed opportunities for vaccination, and helping to identify accessible vaccination services in their community.[4]
Creating supportive health care environments: Vaccination is enabled by supportive health care environments, including access to a trusted physician and culturally safe, person-centred care.[5] Reducing vaccine-related pain and fear can also positively impact vaccination experiences.[4,6]
Fostering supportive vaccine information environments: Not all people have equitable access to supportive information environments. Access to timely and accurate information on the safety and effectiveness of vaccines and the frequency and severity of vaccine-preventable diseases from a trusted source is key for shaping knowledge, attitudes, and beliefs about vaccines.[7] Tailored messages that are appropriate, accessible, easy to understand, and culturally relevant can increase vaccine acceptance and uptake.[3]
Finally, recognizing that low immunization coverage may represent gaps in documentation rather than true vaccination coverage, family physicians are strongly recommended to document vaccines in the Provincial Immunization Registry using one of the provincial tools (eForms,[8] the immunization record portal,[9] or electronic medical record system integrations). People whose records are not reflected in Health Gateway should also be encouraged to submit or update their vaccination records in the provincial immunization record portal.[9]
—Elaine Chan, MPH
Senior Practice Leader and Epidemiologist, Immunization Programs and Vaccine Preventable Diseases Service, BCCDC
—Michelle Takeuchi, RN, MHA
Vaccine Educator, Immunization Programs and Vaccine Preventable Diseases Service, BCCDC
—Jia Hu, MD, MSc, FRCPC, CCFP
Medical Director (Interim), Immunization Programs and Vaccine Preventable Diseases Service, BCCDC
hidden
This article is the opinion of the BC Centre for Disease Control and has not been peer reviewed by the BCMJ Editorial Board.

This work is licensed under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
References
1. BC Centre for Disease Control. Immunization coverage reports. Accessed 7 August 2026. www.bccdc.ca/health-professionals/data-reports/immunizations.
2. BC Centre for Disease Control. Childhood immunization dashboard. Updated 6 August 2026. Accessed 7 August 2026. https://reporting.bccdc.ca/childhood-immunization-coverage-dashboard/.
3. Government of Canada. Vaccination coverage in children. Updated 26 May 2026. Accessed 8 August 2026. https://health-infobase.canada.ca/vaccination-coverage/starvax/children.html.
4. Public Health Agency of Canada. Realizing the future of vaccination for public health. October 2024. Accessed 10 August 2026. www.lakelandsph.ca/media/eiglz1uc/vaccination-in-public-health-report-cpho.pdf.
5. College of Physician and Surgeons of British Columbia. Indigenous cultural safety, cultural humility and anti-racism. Accreditation standards. 1 April 2026. Accessed 10 August 2026. www.cpsbc.ca/files/pdf/NH-AS-Indigenous-Cultural-Safety-Cultural-Humility-Anti-racism.pdf.
6. BC Centre for Disease Control. CARD system for vaccination. Accessed 10 August 2026. www.bccdc.ca/health-professionals/clinical-resources/card-system-for-vaccination.
7. HealthLinkBC. Immunizations. Accessed 10 August 2026. www.healthlinkbc.ca/health-library/immunizations.
8. Government of British Columbia. Provincial eForms solution: eForms launcher. Accessed 10 August 2026. www.eforms.healthbc.org.
9. Government of British Columbia. Submit or update your vaccine record. Accessed 7 August 2026. www.immunizationrecord.gov.bc.ca.
