
Practical tips for interpreting blood culture results
Issue: BCMJ,
vol. 68, No. 8, October 2026
|
Pages 276-278 |
MDs To Be
Exploring the time for blood culture results to be reported, interpreting whether a microorganism is a pathogen or a contaminant, and transitioning patients from intravenous to oral therapy.
Situations that would prompt a clinician to order blood cultures include suspected endocarditis, pyelonephritis, sepsis, and other serious infections.[1,2] Blood culture results provide important clinical information, including identification of the causative organism and its antimicrobial susceptibility. These parameters are central to managing bloodstream infections.
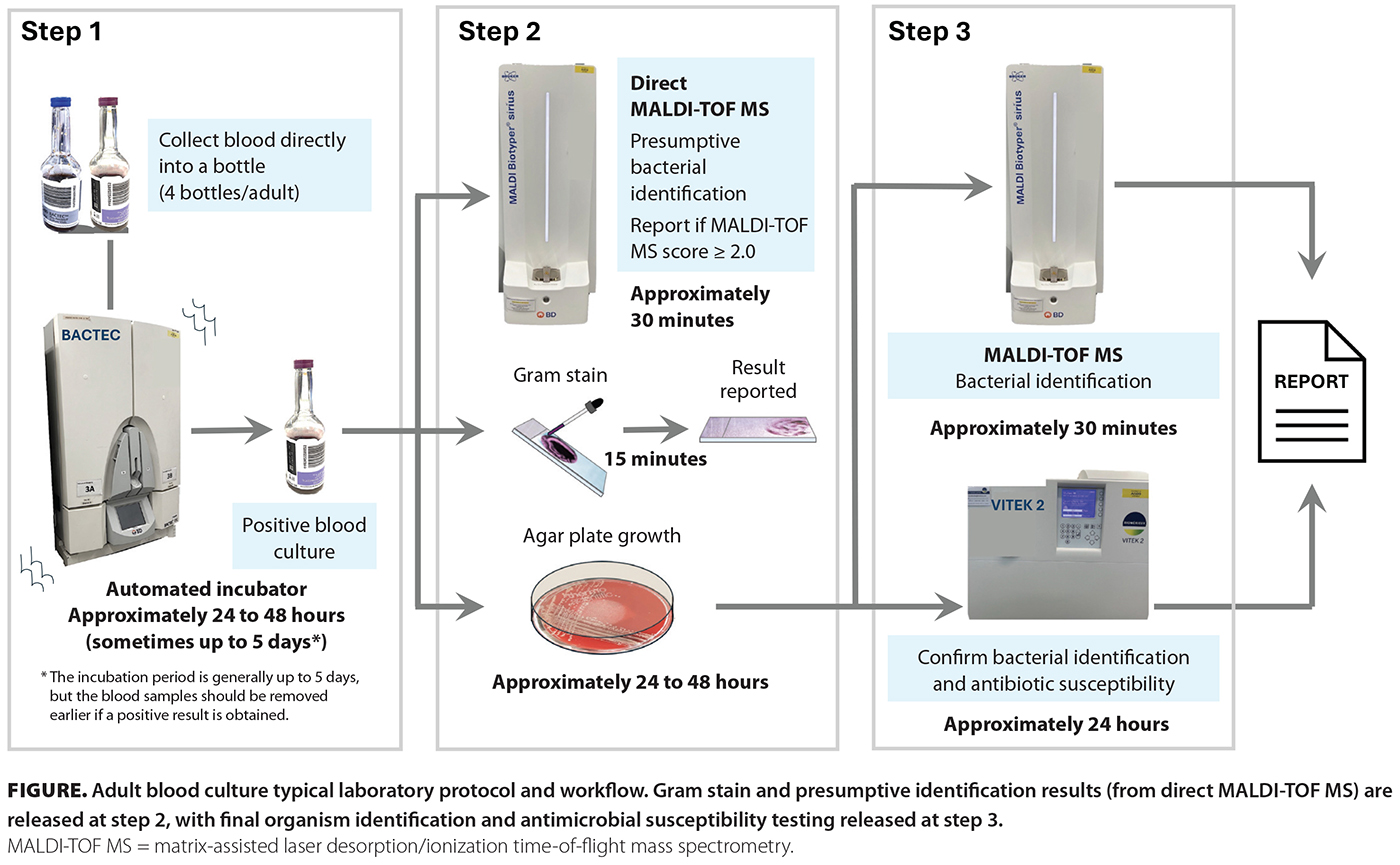
To simplify the interpretation of blood culture results, we address common questions from clinicians, such as why antimicrobial susceptibility results are not available with the initial Gram stain, how to distinguish true infection from contamination, and why oral antibiotic options may not be reported. Using the laboratory workflow shown in the Figure, we aim to help clinicians confidently incorporate blood culture results into clinical decision making.
Timing and interpretation of presumptive blood culture results
In a typical adult blood culture protocol, four blood culture bottles are collected from two venipuncture sites and placed in an automated incubator for up to 5 days [Figure, step 1].[1,2] Although this remains standard practice, emerging evidence suggests that single-site venipuncture sampling may be sufficient in select settings.[3] Most clinically significant bloodstream infections are detected in the first 24 to 48 hours, so cultures that remain negative beyond this point are substantially less likely to yield an infectious organism.[1,4]
Clinically, this timeline helps frame risk. For instance, in patients whose clinical status is improving, negative cultures after 48 hours suggest a lower likelihood of a true bloodstream infection. However, when clinical suspicion remains high—such as in the presence of ongoing fever, hemodynamic instability, or sepsis—empiric antibiotic treatment may be initiated while awaiting blood culture results.
Within 1 hour of a blood culture returning a positive result, the laboratory releases the Gram stain to the ordering clinician. In many cases, the presumptive organism is also identified, using direct matrix-assisted laser desorption/ionization time-of-flight (MALDI-TOF) mass spectrometry [Figure, step 2]. When confidence thresholds are met, a presumptive identification (e.g., “presumptive Staphylococcus aureus”) is released.[1,5] When thresholds are not met, only the Gram stain result is reported, and identification is deferred until final testing [Figure, step 3].
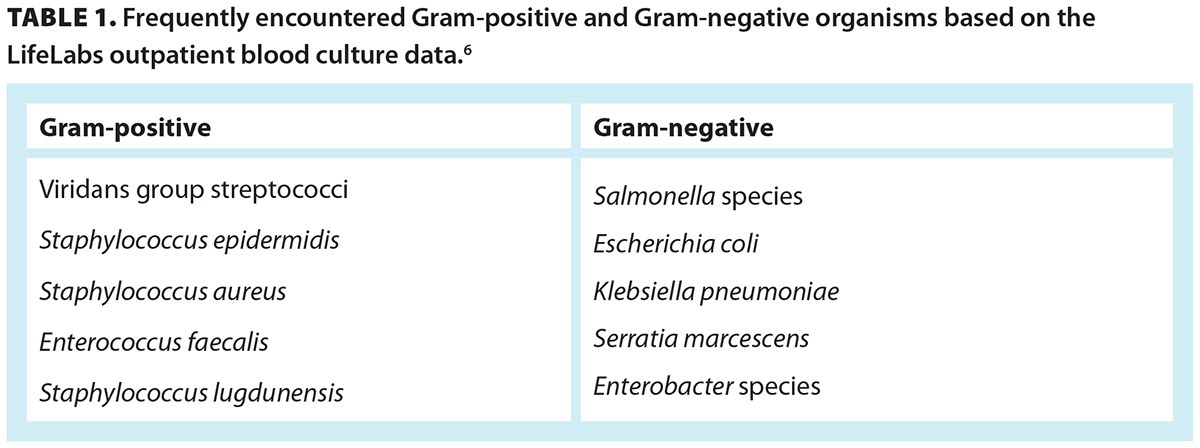
In practical terms, clinicians can expect to receive Gram stain results, with or without presumptive organism identification, within 1 to 2 days of sample submission. At this stage, antimicrobial susceptibility data are not yet available. However, empiric antibiotics may still be selected by combining the Gram stain and presumptive organism identification with antimicrobial susceptibility tables from local laboratories and hospitals. When only Gram stain results are available, published analyses of local epidemiology and susceptibility patterns may inform initial treatment decisions [Table 1]. Table 1 is based on outpatient blood culture data, which represent a subset of bloodstream infections, because blood cultures are more commonly obtained in hospitalized patients with severe illness. For example, analyses of regional bloodstream infections in British Columbia demonstrate that, among Gram-negative organisms, Escherichia coli predominated on Vancouver Island, whereas in the Lower Mainland, Salmonella species were more common than E. coli.[6]
Definitive organism identification and antimicrobial susceptibility testing take longer, as they require subculture to obtain isolated bacterial colonies. This process typically adds another 24 to 48 hours to the testing timeline [Figure, step 3].[2] As a result, antimicrobial susceptibilities are typically available 3 to 4 days after submitting a patient’s sample.
Anticipating this timeline, clinicians can plan follow-up monitoring of the changes in a patient’s clinical status. Once available, the antimicrobial susceptibility can be used to confirm, narrow, or adjust initially selected empiric therapy. Ultimately, the ordering clinician is responsible for reviewing results, notifying patients, and ensuring appropriate follow-up.[7]
Distinguishing true infection from contamination
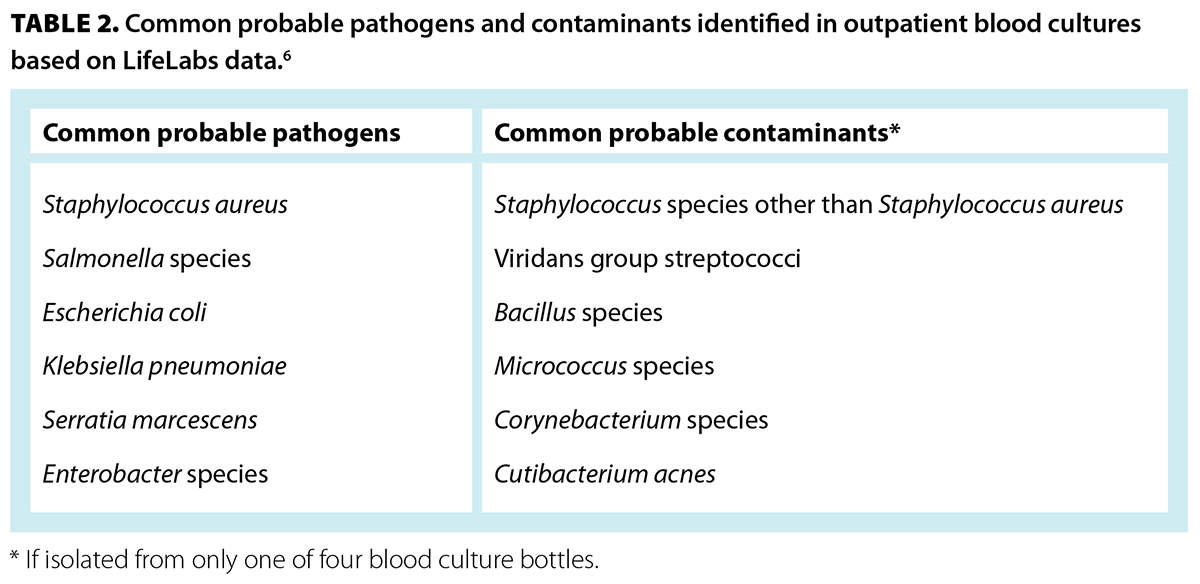
Interpreting preliminary blood culture results requires careful consideration of both the identified organism and the clinical context. Certain organisms are more likely to be contaminants, while others are more often associated with true bloodstream infections.[8] Organisms commonly considered to be contaminants—particularly when isolated from only one of four bottles—include Cutibacterium acnes, Bacillus species, Corynebacterium species, and coagulase-negative staphylococci such as Staphylococcus epidermidis.[2] In most clinical situations, these do not require antibiotic therapy. However, they may represent true infection in patients with intravascular catheters, prosthetic joints or valves, or other implanted devices.
In contrast, isolation of organisms such as Staphylococcus aureus, beta-hemolytic streptococci such as Streptococcus pyogenes and Streptococcus agalactiae, Streptococcus pneumoniae, Enterobacteriaceae species such as E. coli and Klebsiella pneumoniae, Pseudomonas aeruginosa, organisms from the Bacteroides fragilis group, and Candida species should generally be considered clinically significant, even when detected in a single blood culture bottle [Table 2]. These organisms are rarely contaminants and should prompt urgent initiation of intravenous antimicrobial therapy.[1,2]
The patient’s clinical presentation can be used as a consistency check. For example, complicated pyelonephritis that begins with urinary tract symptoms supports a urinary source, where Enterobacteriaceae species, most commonly E. coli, would be expected. In contrast, detection of organisms not typically associated with the presenting syndrome, such as Streptococcus pneumoniae or Streptococcus pyogenes in a presumed urinary source, should prompt consideration of an alternative focus of infection and escalation of care when appropriate.
Transitioning from intravenous to oral therapy
Bloodstream infections generally require initial intravenous antimicrobial therapy. Once the infection is clinically controlled, patients may transition to oral antibiotics to complete therapy, provided specific criteria are met. These criteria include demonstrated susceptibility to an oral agent, hemodynamic stability, adequate source control, and reliable gastrointestinal absorption.[1]
The step-down from intravenous to oral therapy is an important component of antimicrobial stewardship that reduces the burden of prolonged intravenous access and catheter-related complications.[9,10] However, because initial management of bloodstream infections is typically intravenous, oral options are often not reported in antimicrobial susceptibility results unless specifically requested from the microbiology laboratory. Treatment decisions ultimately rest with the ordering clinician and often involve collaboration with infectious diseases and microbiology teams.[7]
Conclusions
Managing bloodstream infections relies on understanding blood culture processing timelines and results. Early interpretation of the Gram stain and presumptive identification of the organism help differentiate contamination from true infection and guide initial therapy. Final test results help identify the pathogens and potentially effective antibiotics. When combined with the patient’s clinical condition and local epidemiology, these results help the care team quickly choose the most appropriate antimicrobial therapy.
Competing interests
Ms Novoseltseva has no competing interests to declare. Dr Yeung has been paid to work as a physician, pharmacist, microbiologist, and clinical assistant professor. Opinions expressed are solely his own and do not represent the views of his employers.
Acknowledgments
The authors thank Dr Romina Reyes, national medical director of LifeLabs, for her direction and support. In addition, they thank all LifeLabs microbiologists, medical laboratory assistants and technologists, and information technology personnel for their technical support. Ms Novoseltseva gratefully acknowledges the financial support of the University of British Columbia Summer Student Research Program, funded by the Department of Pathology and Laboratory Medicine.
hidden
This article has been peer reviewed.

This work is licensed under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
References
1. Miller JM, Binnicker MJ, Campbell S, et al. Guide to utilization of the microbiology laboratory for diagnosis of infectious diseases: 2024 update by the Infectious Diseases Society of America (IDSA) and the American Society for Microbiology (ASM). Clin Infect Dis 2024; ciae104. https://doi.org/10.1093/cid/ciae104.
2. Wilson ML, Kirn TJ Jr, Antonara S, et al. M47: Principles and procedures for blood cultures. 2nd ed. Clinical and Laboratory Standards Institute, 2022.
3. Ekwall-Larson A, Yu D, Dinnétz P, et al. Single-site sampling versus multisite sampling for blood cultures: A retrospective clinical study. J Clin Microbiol 2022;60:e0193521. https://doi.org/10.1128/JCM.01935-21.
4. Yeung E, Sant N, Sucha E, et al. Finding significant pathogens in blood cultures in children: Should we set the timer to 36 hours? J Assoc Med Microbiol Infect Dis Can 2024;9:11-19. https://doi.org/10.3138/jammi-2023-0009.
5. Simon L, Ughetto E, Gaudart A, et al. Direct identification of 80 percent of bacteria from blood culture bottles by matrix-assisted laser desorption ionization-time of flight mass spectrometry using a 10-minute extraction protocol. J Clin Microbiol 2019;57:e01278-18.
6. Novoseltseva P, Yeung EYH. Regional variation in community bacteremia pathogens in British Columbia, Canada. Can J Infect Control 2025;40:172-178. https://doi.org/10.36584/cjic.2025.004.02.172.178.
7. Canadian Medical Protective Association. Test results follow-up. March 2021. Accessed 15 March 2026. www.cmpa-acpm.ca/en/education-events/good-practices/physician-patient/test-results-follow-up.
8. Weinstein MP, Towns ML, Quartey SM, et al. The clinical significance of positive blood cultures in the 1990s: A prospective comprehensive evaluation of the microbiology, epidemiology, and outcome of bacteremia and fungemia in adults. Clin Infect Dis 1997;24:584-602. https://doi.org/10.1093/clind/24.4.584.
9. Tamma PD, Conley AT, Cosgrove SE, et al. Association of 30-day mortality with oral step-down vs continued intravenous therapy in patients hospitalized with enterobacteriaceae bacteremia. JAMA Intern Med 2019;179:316-323. https://doi.org/10.1001/jamainternmed.2018.6226.
10. Barlam TF, Cosgrove SE, Abbo LM, et al. Implementing an antibiotic stewardship program: Guidelines by the Infectious Diseases Society of America and the Society for Healthcare Epidemiology of America. Clin Infect Dis 2016;62:e51-e77. https://doi.org/10.1093/cid/ciw118.
hidden
Ms Novoseltseva is a medical student at the University of British Columbia. She holds an MSc in chemistry from Queen’s University in Kingston, Ontario, and worked as an associate medicinal chemist in the pharmaceutical industry prior to entering medical school. Dr Yeung has worked as a medical microbiologist at LifeLabs, a community pharmacist, and a clinical assistant professor in the University of British Columbia Faculty of Pharmaceutical Sciences and Faculty of Medicine and Simon Fraser University’s Stephens Family School of Medicine.